COVID-19 outcome disparities in US cities
Black and Latino excess mortality linked to frontline jobs and comorbidity — not mystical racial immunity.
HLA and immune genes are hyper-diverse within communities — the opposite of tidy racial immune types.
Last reviewed Sources & creditsMedia creditsMethodology
Five research punchlines — scan before you dive.
Pathogens favor immune gene diversity; neighbors often differ at HLA more than stereotypes allow.
Transplant medicine matches alleles, not folk races.
Use this page to deflate “racial immunity” talk.
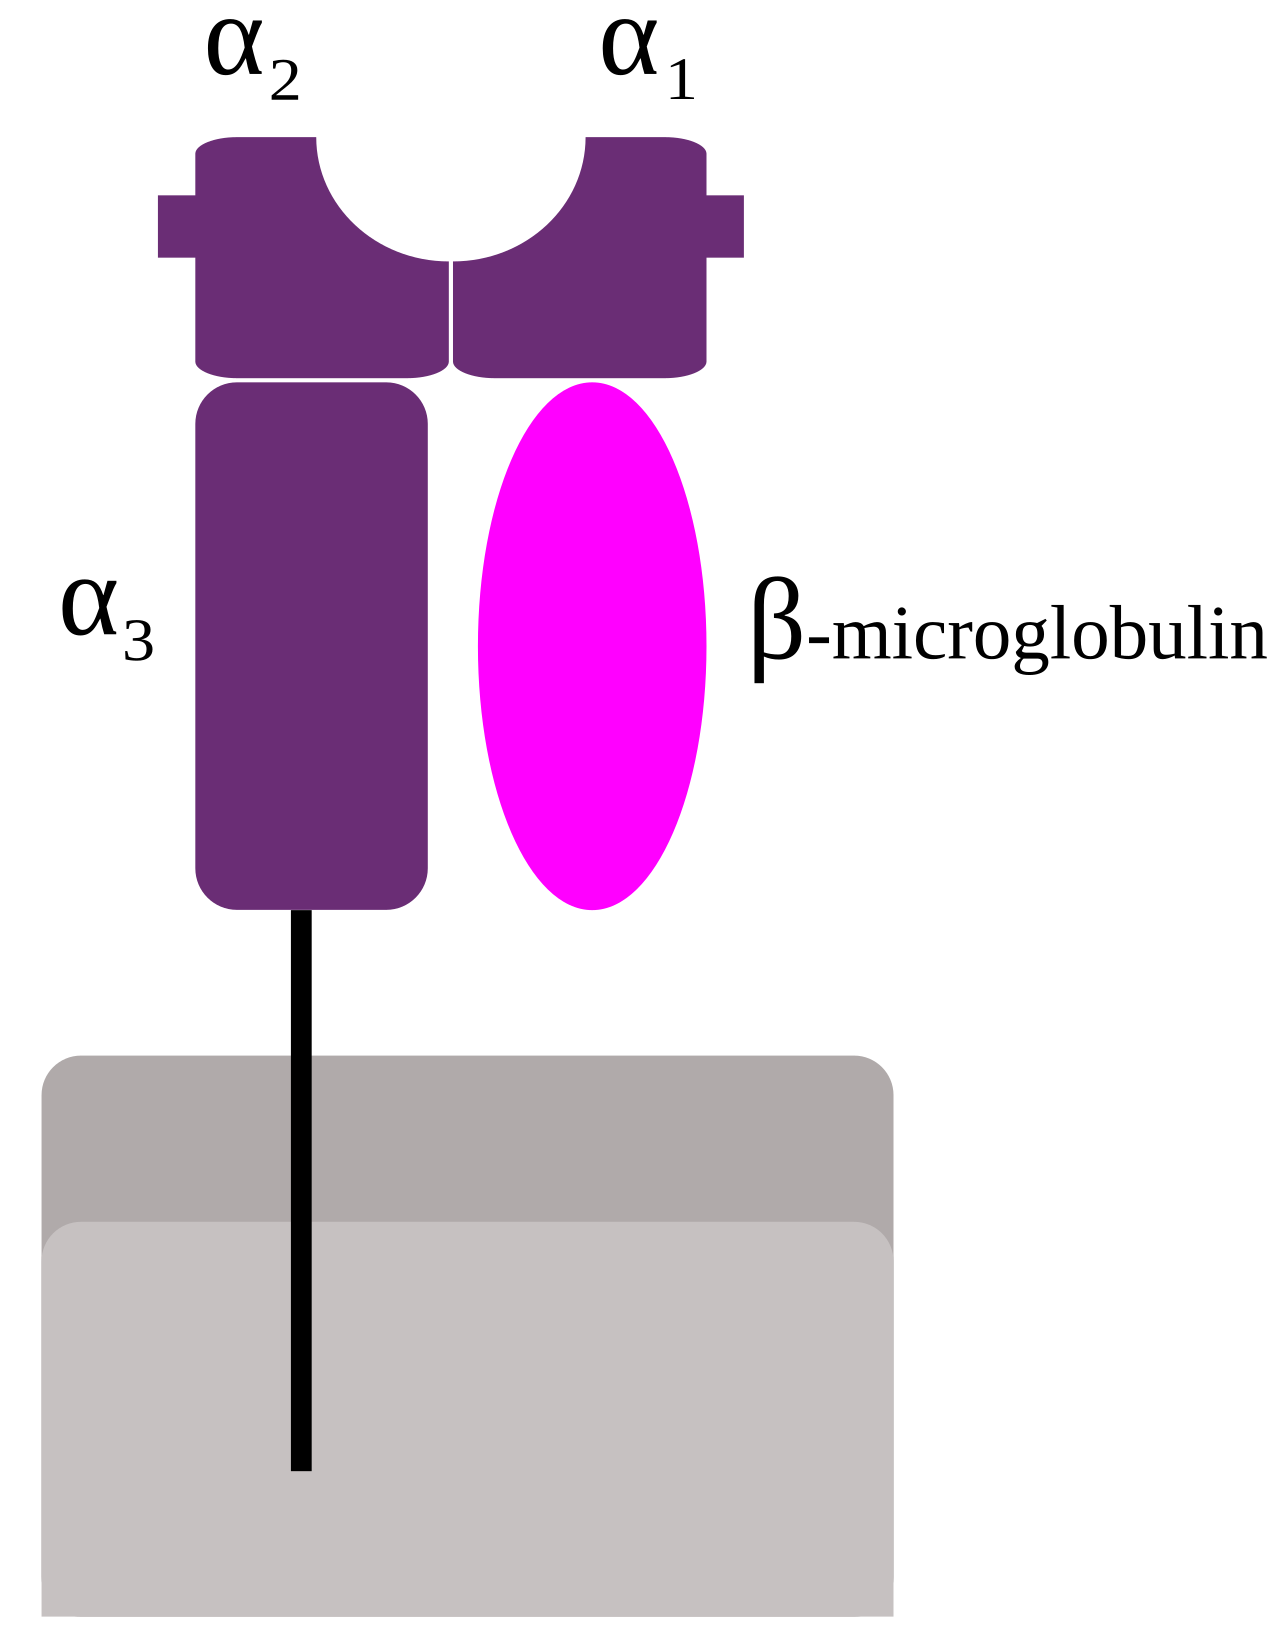
Pathogen-driven polymorphism.
HLA molecules present peptides to T cells; many alleles mean many presentation styles.
Heterozygote advantages are often hypothesized under infection pressure.
Local pathogen histories, global overlap.
Allele frequencies differ by region because epidemics and demography differed.
Overlap between regions is massive — individuals are not their chart cell.
Concrete histories of adaptation and contact — never a league table of peoples.
Black and Latino excess mortality linked to frontline jobs and comorbidity — not mystical racial immunity.
Founder alleles in small populations illustrate history, not superiority or defect ranking.
Endemic arboviruses shaped local HLA frequencies — geography of pathogens, not "tough races."
Age and immunosenescence dominate more than self-identified race — precision beats folklore.
Scholarly themes rewritten for curious readers — not paywalled jargon, and never a race ranking.
MHC/HLA loci are among the most diverse in the genome — within communities, not between cartoon races.
Takeaway Your neighbor’s HLA may surprise you.
Models suggest infection pressures help maintain many alleles; stories remain actively tested.
Takeaway Germs shape immune menus.
Matching HLA alleles matters; self-identified race is a blunt, often misleading proxy.
Takeaway Type the locus, not the census box.
Analyses emphasize exposure, comorbidity and healthcare access over mystical racial immunity.
Takeaway Inequality infected outcomes.
People differ in vaccine responses for many reasons; race is a poor summary statistic.
Takeaway Precision beats folklore.
Books, reviews and museum trails — starting points, not a syllabus.
HLA stories told for lay readers — hyperdiversity within communities.
Germs shape immune menus — active research, not racial immunity myths.
Donor matching drives solidarity campaigns — alleles, not census boxes.
COVID disparities traced to exposure and care access — inequality infected outcomes.
Official allele nomenclature — precision for transplant, not folk race.
Tap a card — the fact stays hidden until you flip.
Some races are immune to disease X.
Immunity is not a racial essence; exposure and care dominate.
HLA proves biological races.
Extreme within-group diversity undercuts race taxonomy.
Transplant matching equals race matching.
Allele matching is the clinical act.
Pandemic outcomes prove hierarchy.
Social determinants explain far more.
One blood type chart sorts immunity.
Immune genetics is broader and individual.
Human immune genetics is individual and local. Folk races are bad medical categories.
Pathogen pressure and mating patterns maintain many alleles.
Outcomes track exposure, comorbidity and health systems more than mystical race immunity.
Matching is allelic; ancestry may correlate weakly but clinicians type alleles.
See malaria-adaptations — classic selection stories, still not race ranks.
Public health logistics beat genetic fatalism.
Malaria-adaptations; genetic-structure; race-is-not-biology.
Genetic immunology data is sensitive — consent matters.